

Can Touch Be a Form of Knowledge?
A hand on the chest or neck may not diagnose what is wrong. But it can change what becomes perceptible—and that may be a kind of knowledge modern life too easily neglects.

A person presses the heel of a hand into the tight ridge between neck and shoulder. Another rests a palm over an unsettled stomach before a difficult conversation. A runner rolls a calf after training; a parent pats an infant’s back; a worshipper places a hand over the heart. None of these gestures can reliably announce, this is the disease. Yet they often seem to ask a real question: What is happening here, now, in this body?
Touch is not a diagnostic oracle. A tender abdomen does not tell us its cause; chest pressure should never be interpreted away through self-soothing; persistent or severe symptoms deserve medical assessment. But between the false choices of “the body knows everything” and “subjective sensation knows nothing,” there is a more useful possibility. Touch can be a method of bodily inquiry: a way of altering attention, locating sensation, testing tolerance, and discovering what a person can or cannot comfortably do in a particular moment.
The three steps that should not be confused
Interoception is the ongoing sensing and integration of internal bodily signals: breathlessness, heartbeat, nausea, temperature, hunger, muscular effort, visceral discomfort. It is not a single, infallible inner sense. Research describes it as a family of processes involving sensing, attention, interpretation, memory and regulation, much of it outside conscious awareness. A hand on the body can make a vague signal easier to notice, but noticing is only the first step. Interoception and Mental Health: A Roadmap
Interpretation comes next: “My stomach is clenched because I am anxious”; “this neck tension means I slept badly”; “the heaviness in my chest is grief.” Such readings can be insightful, provisional, or mistaken. They draw on memory, culture, fear, expectation and context as much as on the raw sensation itself. Diagnosis, by contrast, is a medically actionable judgment that requires patterns of evidence—history, examination, testing, and sometimes urgent exclusion of dangerous conditions. The ethical discipline is simple: let touch inform a question, not settle a verdict.
What contact changes
Touch adds an external sensation to an internal one. That sounds trivial, but it can reorganize experience. A slow stroke, steady pressure, warmth, or the containment of a hand can give attention a boundary: not “I feel terrible everywhere,” but “there is a knot here,” “my breathing shifts when I soften my shoulders,” or “this contact is too much.” In hairy skin, gentle stroking at particular speeds can recruit C-tactile afferents—unmyelinated sensory fibers associated with the affective qualities of touch. Their activity is related to pleasantness more than precise localization; but affective touch is not reducible to a single nerve type, and it is not universally pleasant. What are C-tactile afferents and how do they relate to “affective touch”?
That final qualification matters. The same hand on the same forearm can register as care, interruption, invasion, flirtation, threat, or nothing in particular. Studies of social touch find that its experience is strongly shaped by relationship, setting, group membership, psychological state, and features of the toucher. Touch is therefore not merely a stimulus delivered to skin; it is an event interpreted by a person with a history. Social touch experience in different contexts: A review
Relief is not the opposite of knowledge
Massage, acupressure and athletic recovery rituals are often judged by a narrow question: did they mechanically “fix” tissue? That is sometimes the wrong unit of analysis. Relief can emerge through a combination of local pressure, movement, rest, attention, expectation, interpersonal safety, and a temporary lowering of alarm. This does not make relief imaginary. It means that pain and comfort are lived, nervous-system-mediated experiences rather than simple readouts of structural damage.
The clinical evidence also asks for modesty. A recent overview of systematic reviews found some moderate-certainty evidence that massage is associated with pain benefit in selected conditions, but no high-certainty conclusions, and evidence that it outperforms other active therapies was rare. Massage can be a reasonable comfort or symptom-management tool for some people; it should not be sold as a universal mechanism for detecting or correcting hidden bodily faults. Use of Massage Therapy for Pain, 2018-2023: A Systematic Review
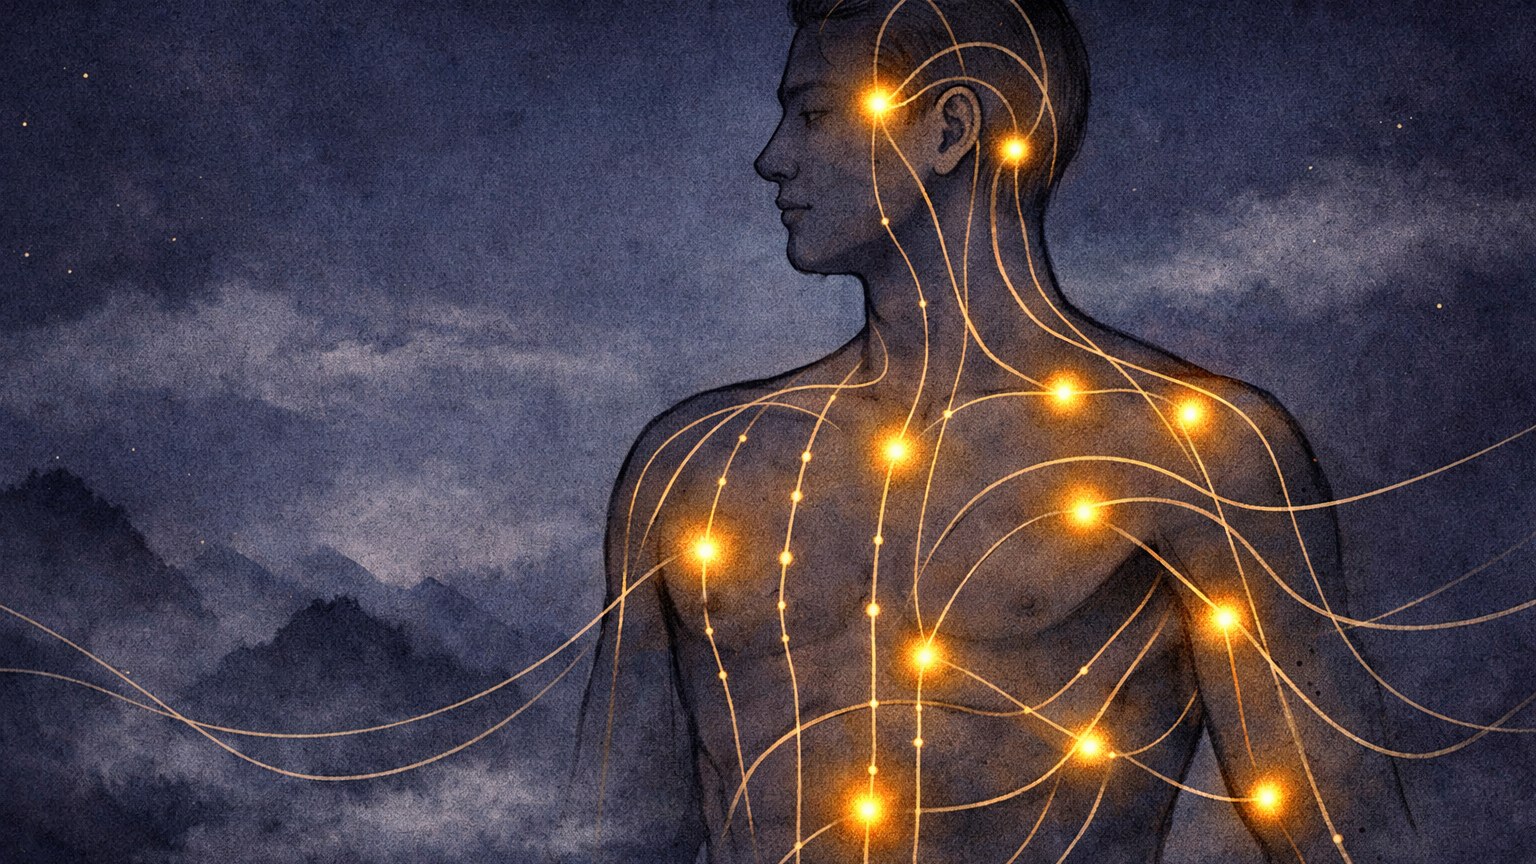
Acupressure raises the issue especially clearly. Within Chinese medical traditions, the body is mapped through channels and points; an annotated translation of the Huang Di Nei Jing Su Wen uses the phrase “qi pressing” in a discussion of attending to the arrival of qi. That is a meaningful vocabulary within its own historical medical world, not a finding that modern physiology has confirmed as a measurable energy flowing through meridians. Contemporary trials may investigate symptom outcomes without adjudicating the metaphysics. For primary dysmenorrhea, one recent review reported pain reductions across trials but judged the overall evidence low quality—an invitation to neither dismiss patients’ relief nor turn a tradition’s explanatory language into settled biomedical fact. Huang Di Nei Jing Su Wen : An Annotated Translation of Huang Di’s Inner Classic – Basic Questions, Volumes 1 and 2 Efficacy and safety of acupressure for primary dysmenorrhea: A systematic review and meta-analysis of randomized controlled trials
Calling part of an intervention “placebo” can obscure more than it clarifies. In ordinary speech, placebo means fake. In research, contextual effects include expectation, learned associations, clinical ritual, communication and the meaning a person gives to care. Those forces can alter reported symptoms and pain sensitivity; they do not prove that a practitioner has discovered the cause of pain, nor do they make the change contemptible. A better question is: What did this encounter alter—tissue load, attention, fear, expectation, social safety, behavior, or some mixture?
The lived body is not a machine with bad data
Phenomenology supplies language for what medical measurement can miss without displacing it. Maurice Merleau-Ponty distinguished one’s own body from the body treated solely as an object among objects. The point is not anti-science. It is that my shoulder is not initially a set of structures I inspect from the outside; it is where reaching, turning, bracing, fatigue and possibility are lived. In the newer translation of Phenomenology of Perception, the body is described as the center from which objects become available through movement and as a body lived as one’s own rather than possessed like an object. Phenomenology of Perception
Under that view, a hand on the sternum does not reveal a secret organ-message hidden beneath consciousness. It may instead change the field in which experience appears. The chest can become not just “where anxiety is,” but a place where one detects shallow breathing, grief, guardedness, or simply the wish to pause. This is knowledge in a deliberately limited sense: situated, first-person, revisable knowledge of one’s present relation to strain, comfort and capacity.
Here is the stranger, more metaphysical possibility—offered as interpretation, not empirical conclusion. Perhaps caring touch sometimes reveals that the self is less like a sealed observer inside a body than a living threshold: sensing is already a relationship between skin, memory, gravity, other people and world. In caregiving, touch can make this especially visible. An infant does not first form a complete private state and then communicate it; soothing may be partly co-regulated through rocking, patting, holding and timing. A small home-observation study found that, among several kinds of parent–infant contact, soothing touch was associated with immediate increases in an index of infants’ parasympathetic activity—while other infant studies have found null effects for particular skin-to-skin interventions and outcomes. The lesson is not that touch possesses mystical power; it is that regulation is relational, variable and not captured by one outcome measure. Soothing touch matters: Patterns of everyday mother-infant physical contact and their real-time physiological implications
Consent is part of the knowledge
A body is not made more knowable by being overridden. For trauma survivors, people with sensory sensitivities, those in pain, and anyone whose boundaries have been ignored, touch may intensify vigilance rather than settle it. Cultural norms and personal histories also shape which contact is welcome, from whom, where, and under what conditions. A practitioner, coach, caregiver or partner should ask rather than infer; specify where and how; accept “no” without explanation; and remember that consent can change midway through an interaction.
Self-touch is not automatically safer. It can become a compulsive surveillance system: checking the pulse, scanning the abdomen, repeatedly testing a muscle, demanding certainty from every flicker. The aim is not maximal bodily attention. It is usable attention—enough to notice a limit, enough to choose rest or movement, enough to seek help when warranted, and enough to return to the world rather than endlessly monitor oneself.
So can touch be knowledge? Yes, if we mean neither diagnosis nor supernatural proof. It can be knowledge of texture, threshold, permission, need and change: “this is tender,” “I am more activated than I thought,” “I want less pressure,” “my breath returns when I slow down.” Medicine is right to resist turning these reports into premature pathology. But a culture that treats them as noise risks producing a person who has measurements of the body without any practiced relationship to inhabiting it. The hand on the neck does not have to know what is wrong. Sometimes its quieter achievement is teaching us how to ask.
Sources and references
- Interoception and Mental Health: A Roadmap
- What are C-tactile afferents and how do they relate to “affective touch”?
- Social touch experience in different contexts: A review
- Use of Massage Therapy for Pain, 2018-2023: A Systematic Review
- Efficacy and safety of acupressure for primary dysmenorrhea: A systematic review and meta-analysis of randomized controlled trials
- Huang Di Nei Jing Su Wen : An Annotated Translation of Huang Di’s Inner Classic – Basic Questions, Volumes 1 and 2
- Phenomenology of Perception
- Soothing touch matters: Patterns of everyday mother-infant physical contact and their real-time physiological implications
More to read
10 Lesser-Known Acupuncture Points: A Map of Pathways, Thresholds and Traditional Use
Beyond the famous hand and leg points lies a quieter acupuncture map: ten classical sites whose locations, po…
10 Lesser-Known Acupuncture Points: A Map of Crossroads, Reservoirs and Hidden Pathways
Beyond acupuncture’s familiar headline points lies a quieter set of locations that reveal how Traditional Chi…

Can Touch Be a Form of Knowledge?
A hand on the neck, stomach, or chest can change more than discomfort. It can make sensation legible—without …
Apps to use

Fu Hsi's Name Trigram
Discover the trigram hidden within your name and explore its personality traits, strengths, weaknesses, caree…

Fu Hsi's Octogram
Discover your birth trigram, explore your current life phase, and search past or future phases through Fu Hsi…

Chinese Zodiac
Discover your Chinese zodiac animal and element from your birth date, and explore its traditional traits, str…